Surgical table

Home Blogs

Surgical table

  • Electric vs. Hydraulic Surgical Table: Which Drive System Is Right for Your OR?
    Sep 07, 2026
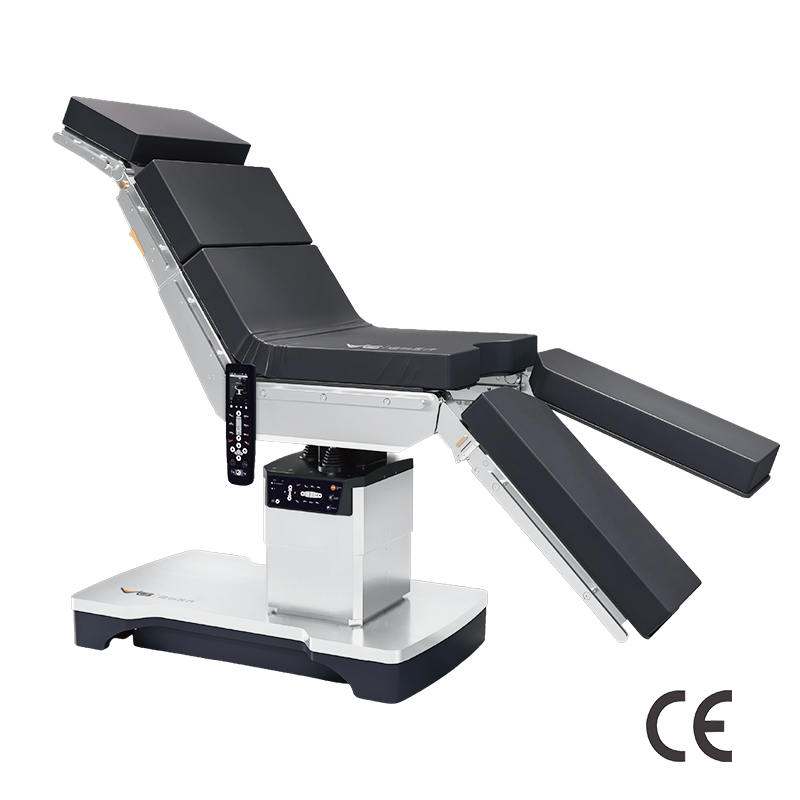
    Electric surgiacal table COMFORT 2000 Series Best for Day Surgery/ Outpatient Electric hydraulic surgical table COMFORT 300 Series Best for general OR/ Proven workhorse Electric hydraulic surgical table Vcare 7000 Series Vcare 5000 Series Best for Central OR       Ask most OR procurement teams what separates one surgical table from another, and the answer usually comes down to the drive system: electric or hydraulic. It sounds like a technical detail, but it is the single decision that shapes how the table performs, how much it costs to run, and which surgical specialties it can serve. This guide breaks down how the two systems work, their real-world trade-offs, and a simple framework for deciding which one fits your operating room. How the Two Drive Systems Work   The difference is in what makes the table move. Electric surgical tables use electric motors and actuators to drive every movement — height, tilt, Trendelenburg, and section articulation. Control is electronic, typically through a hand pendant, remote, or integrated OR control system. Hydraulic surgical tables use pressurized fluid. A pump (manual foot pump or electric pump) forces oil into cylinders, which extend to raise or position the table. The fluid does the heavy lifting. A third option — the electro-hydraulic table — combines both: electric control with hydraulic power. It deserves its own section below, because it is the workhorse of heavy-load surgery. Electric Surgical Tables: Pros and Cons   Electric tables are the default in most high-volume, general-purpose operating rooms today. Pros: ·        Precise, repeatable positioning — motor control allows fine micro-adjustments that hydraulic tables struggle to match. ·        Fast — smooth, quick transitions between positions speed up room turnover. ·        Quiet — no pump noise, which matters in delicate procedures and patient comfort. ·        Programmable — many models store position presets and integrate with digital OR systems. ·        Clean and low-maintenance — no hydraulic fluid to leak or seals to replace. Cons: ·        Higher upfront cost — motors, actuators, and control electronics add to the price. ·        Power dependency — needs a stable electrical supply; battery backup is recommended. ·        Load limits — standard electric tables may have lower articulated load capacity than electro-hydraulic equivalents. Electric tables are the right starting point for general surgery, gynecology, urology, ENT, and other specialties that reward speed and precision. Hydraulic Surgical Tables: Pros and Cons   Pure hydraulic tables are less common in high-end ORs but still fill a real niche. Pros: ·        Lower upfront cost — fewer electronic components mean a cheaper purchase. ·        High load capacity — hydraulic cylinders excel at lifting heavy patients smoothly. ·        No power required (manual models) — a foot or hand pump works even during outages. Cons: ·        Slower and less precise — positioning is coarser, and fine adjustments are harder. ·        Physical effort — manual pumping is tiring for staff. ·        Maintenance — seals and fluid lines can leak and need periodic service. ·        Less integration — limited programmability and digital OR connectivity. Hydraulic tables suit lower-budget facilities, backup units, or settings with unreliable power — not the high-turnover core of a modern surgical department. Electro-Hydraulic: The Hybrid Worth Knowing   If your case mix includes orthopedics, trauma, bariatrics, or any heavy-load work, the electro-hydraulic table is often the best answer. It uses an electric pump to pressurize the hydraulic system, giving you: ·        The load capacity and stability of hydraulics. ·        The electric control and precision of a motorized table. ·        Smooth, jerk-free height travel — important when positioning an anesthetized patient. The trade-off is cost and slightly higher maintenance than a pure electric table. But for heavy patients and demanding positions, that trade-off is almost always worth it. Side-by-Side Comparison   Criterion Electric Electro-hydraulic Hydraulic Positioning precision High High Medium Load capacity Medium–High Highest Medium–High Speed Fast Medium Slow Noise Low Low–Medium Medium Power dependency Full Partial None (manual) Maintenance Lower Moderate Moderate Digital OR integration Strong Strong Limited Upfront cost Higher Higher Lower How to Decide: A Simple Decision Framework   Run your case mix through these three questions: 1. Do you perform heavy-load or orthopedic cases?Yes → electro-hydraulic. No → keep going. 2. Is room turnover speed and precision your priority?Yes → electric. A busy general OR that runs many short cases wins with electric speed. 3. Is budget tight or power unreliable?Yes → hydraulic (or electric with battery backup). A manual hydraulic table can serve as a low-cost backup or in resource-limited settings. The short version: ·        General surgery, high turnover → electric ·        Orthopedics, trauma, bariatrics → electro-hydraulic ·        Tight budget, backup, unstable power → hydraulic Cost and Maintenance: The Real Difference   Purchase price is only part of the story. ·        Electric tables cost more up front but less to maintain — no fluid, fewer seals. Over a 10–15 year life, they often come out ahead in total cost of ownership for high-volume ORs. ·        Electro-hydraulic tables add the hydraulic system back in, so expect periodic seal and fluid service. The cost is justified by what they enable for heavy-load surgery. ·        Hydraulic tables are cheapest to buy, but manual operation adds staff effort and slower turnover, which is a hidden cost in a busy department. Always ask the supplier about local spare parts, service response time, and warranty coverage before committing — a table that is cheap to buy but hard to service will cost more over its lifetime. Frequently Asked Questions   Which is better, an electric or hydraulic surgical table?It depends on your case mix. Electric tables are faster, more precise, and better for high-volume general surgery. Hydraulic (or electro-hydraulic) tables excel at heavy load capacity, making them better for orthopedics and bariatrics. What is an electro-hydraulic surgical table?An electro-hydraulic table combines an electric pump with hydraulic cylinders. It delivers the heavy load capacity of hydraulics with the electric control and precision of a motorized table — the preferred choice for orthopedic and bariatric surgery. Do electric surgical tables work during a power outage?Most electric tables require power to move and should have a battery backup. Manual hydraulic tables can be operated without electricity, which is useful in settings with unreliable power. Are hydraulic surgical tables cheaper to maintain?Not necessarily. Hydraulic systems have seals and fluid lines that can leak and need periodic service. Electric tables avoid hydraulic fluid entirely and are often lower-maintenance over their lifetime. How do I choose between the three types?Use this rule of thumb: electric for general surgery and high turnover, electro-hydraulic for orthopedics and heavy loads, and hydraulic for tight budgets or backup use. For a full evaluation of all factors, see our guide on how to choose a surgical table. The Right Drive System Depends on Your Cases   There is no universally "best" surgical table — only the best table for your case mix. Electric wins on speed and precision; electro-hydraulic wins on load and stability; hydraulic wins on upfront cost and power independence. At VG Medical, we manufacture electric, electro-hydraulic, and hydraulic operating tables — including the VCARE 5000 and VCARE 7000 series — all MDR CE certified and built on modular platforms. Whatever your specialties, we can help you match the drive system to the work you actually do. Not sure which drive system fits your OR? Contact our team with your case mix and load requirements, and we'll recommend the right table.  
  • How to Choose a Surgical Table: The Complete Buyer's Guide
    Sep 02, 2026
    how to choose a surgical table — the types, the seven factors that matter most, and the questions to ask before you sign. Choosing a surgical table is one of the most consequential equipment decisions an operating room team will make. The table is not a passive piece of furniture — it positions the patient, supports surgical access, and either enables or limits the imaging, specialty procedures, and workflow efficiency of your entire OR.   Yet buying teams often default to the cheapest quote or the brand they already know, without first defining what the table actually needs to do. This guide breaks down exactly how to choose a surgical table — the types, the seven factors that matter most, and the questions to ask before you sign. Why the Right Surgical Table Matters A surgical table directly affects three things your hospital is measured on: Patient safety — load capacity, stability under load, and fail-safe operation reduce the risk of intraoperative injury or equipment failure. Surgical precision and access — positioning range, articulation, and imaging compatibility determine whether your surgeons can do their best work.  Long-term return on investment (ROI) — a modular, serviceable table adapts to new specialties and keeps earning years after purchase, while a rigid one gets relegated to storage.   The wrong choice shows up as hidden cost: a table that cannot take a C-arm, an under-sized table that limits bariatric cases, or a drive system that cannot be serviced locally. Know the Main Types of Surgical Tables Before comparing brands, understand the categories. Surgical tables are generally grouped by drive system and by design architecture.   By drive system: Type How it moves Best for Electric (electromechanical) Motors drive all movements High-volume ORs, precise micro-adjustments, remote control Electro-hydraulic Electric pump + hydraulic cylinders Heavy load capacity, smooth height travel, stability Hydraulic (manual pump) Foot/hand pump pressurizes oil Lower cost, areas with unstable power Manual (mechanical) Hand cranks Low-cost backup, limited budget       Electric Hydraulic Table Best for Flagship Central OR  Heavy load capacity, smooth height travel, stability   Electric Table Best for Day Surgery and Outpatient High-volume ORs,precise micro-adjustments remote control   Manual Surgery Table Basic surgical needs  Low-cost backup, limited budget This product has been largely phased out   By architecture:   Fixed-top tables — single, integrated tabletop; robust and cost-effective for standard procedures.  Modular tables — interchangeable tabletops and attachments (orthopedic, urology, C-arm carbon-fiber tops); one base serves many specialties. Most modern hospitals standardize on electric or electro-hydraulic modular tables, which is why the rest of this guide focuses there. 7 Factors to Evaluate Before You Buy 1. Load Capacity and Patient Weight Range Load capacity is a safety spec, not a marketing number. Look for three figures: ·        Rated lifting capacity — the maximum weight the table can safely raise, typically 250–450 kg on modern electro-hydraulic tables. ·        Static load capacity — what the table holds when stationary (often higher than lifting capacity). ·        Articulated load capacity — the weight the table can support while tilted or flexed, which is usually lower. If your facility serves bariatric patients, confirm the table can articulate under high load without binding or strain — this is where cheaper hydraulic units often fall short. 2. Positioning Range and Tabletop Articulation Positioning flexibility is what separates a general table from one that can handle orthopedics, urology, neurosurgery, and gynecology. Evaluate: ·        Height range — low enough for seated/ophthalmic work, high enough for tall surgeons; typical range is 600–1,000 mm. ·        Trendelenburg and reverse Trendelenburg — degree of tilt for vascular, gynecologic, and laparoscopic cases. ·        Lateral tilt and back/leg section articulation — the more independent sections, the more positions you can configure. ·        Sliding tabletop (longitudinal travel) — critical for C-arm imaging clearance. Ask for the full positioning specification sheet, not a brochure photo. 3. Imaging Compatibility (C-Arm and X-Ray) If you do fluoroscopy, trauma, or minimally invasive surgery, imaging compatibility is non-negotiable. Two things to verify: ·        Radiolucent window — the tabletop must be transparent to X-rays along the imaging path. Carbon-fiber tabletops provide the best image clarity with minimal artifact. ·        C-arm clearance — the base and column must not block the C-arm as it sweeps under and around the table. Sliding tops and open-base designs are essential here. A table that is not C-arm compatible effectively locks your OR out of a growing share of procedures. 4. Modularity and Specialty Attachments A modular platform protects your investment. A single base that accepts interchangeable tops — orthopedic traction, urology/lithotomy, carbon-fiber imaging, bariatric — lets one table serve multiple specialties instead of buying three tables. When evaluating modularity, check how quickly attachments swap, whether the locking mechanism is secure, and how many accessory positions are available. 5. Drive System: Electric vs. Hydraulic vs. Electro-Hydraulic This is often the deciding factor. Quick comparison: ·        Electric (electromechanical) — fast, precise, quiet; ideal for high-turnover ORs. Slightly higher upfront cost but lower maintenance. ·        Electro-hydraulic — best load capacity and smoothness; excellent stability under heavy patients; the workhorse of orthopedics and bariatrics. ·        Pure hydraulic — lower cost, no reliance on power; but slower, less precise, and heavier to operate. Choose based on your case mix and power reliability, not on sticker price alone. 6. Infection Control and Cleanability Surgical tables are high-touch surfaces in a sterile environment. Prioritize: ·        Seamless, gap-free surfaces — fewer crevices for fluid and pathogens to collect. ·        Antimicrobial or non-porous coatings — easy to wipe down between cases. ·        Removable pads and rails — cleanable or sterilizable components. ·        Rounded edges and smooth welding — reduces residue traps and makes wiping faster. Faster, more reliable cleaning means faster room turnover and lower infection risk. 7. Safety Certifications and Standards Compliance Do not compromise here. Confirm the table is certified for your market: ·        MDR CE certification — mandatory for the EU and widely accepted globally. ·        IEC 60601 series — electrical safety for medical electrical equipment. ·        ISO 13485 — quality management system for medical devices. Certifications are evidence that the manufacturer's design, materials, and quality system have been independently audited — not just claimed. Electric vs. Hydraulic: Which One Fits Your OR?   Criterion Electric Electro-hydraulic Hydraulic Precision High High Medium Load capacity Medium–High Highest Medium Speed Fast Medium Slow Power dependency Full Partial None (manual) Maintenance Lower Moderate Moderate Upfront cost Higher Higher Lower   Bottom line: for a busy general OR, an electric table gives speed and precision. For orthopedics, bariatrics, and heavy-load work, electro-hydraulic is the safer bet. Pure hydraulic suits lower-budget or power-unstable settings. Total Cost of Ownership: Look Beyond the Sticker Price A surgical table's real cost is spread over 10–15 years of service. When comparing quotes, factor in: ·        Serviceability — are spare parts and trained technicians available in your region? A table that needs to be shipped overseas for repair has a hidden cost. ·        Warranty and support — what is covered, and for how long? ·        Training — does the supplier train your OR staff on safe operation and positioning? ·        Upgradeability — can you add modular tops later without replacing the base? ·        Durability — check materials, welding quality, and rated duty cycles. A cheaper table that is down for a month or cannot be upgraded costs far more than the savings. Red Flags to Watch Out For ·        Vague or missing load specifications — if the seller cannot provide rated/static/articulated load figures, walk away. ·        No imaging clearance documentation — ask for C-arm clearance drawings, not assurances. ·        No local service network — a great price means nothing if repairs take months. ·        Certifications not verifiable — ask for certificate numbers you can check against the issuer. ·        Limited positioning range — a table that cannot tilt or articulate will limit your surgeons. Surgical Table Selection Checklist ·        Rated lifting capacity meets your heaviest patient class ·        Articulated load capacity documented ·        Positioning range covers all your specialties (height, Trendelenburg, lateral tilt) ·        C-arm compatible, with radiolucent window and documented clearance ·        Modular attachments available for future specialties ·        Drive system matches your case mix and power reliability ·        Seamless, cleanable surfaces for infection control ·        MDR CE and IEC 60601 certified (verifiable certificate numbers) ·        Local service, spare parts, and staff training available ·        Transparent total cost of ownership, not just purchase price Frequently Asked Questions What is the standard weight capacity of a surgical table?Most modern surgical tables have a rated lifting capacity between 250 kg and 450 kg, with static load capacity often higher. Always confirm the articulated load capacity if you serve heavier patients, since the table must be able to tilt and flex safely under load. What is the difference between an electric and a hydraulic surgical table?An electric table uses motors for precise, fast, quiet positioning and needs a power supply. A hydraulic table uses pressurized fluid (operated by pump or electric pump) for high load capacity and smooth travel. Electro-hydraulic tables combine both: electric control with hydraulic lifting power, which is ideal for heavy-load work like orthopedics. Are surgical tables compatible with C-arm imaging?Not all of them. C-arm compatibility requires a radiolucent tabletop (often carbon-fiber) and an open base or sliding top that gives the C-arm clearance to sweep around the patient. If you perform fluoroscopy or minimally invasive surgery, make C-arm compatibility a hard requirement. What certifications should a surgical table have?For most global markets, look for MDR CE marking (EU), IEC 60601 electrical safety compliance, and ISO 13485 quality management. Ask for verifiable certificate numbers rather than relying on marketing claims. How often should a surgical table be serviced?Follow the manufacturer's schedule, but plan for at least an annual inspection of the drive system, hydraulic seals, electrical safety, and positioning mechanisms. Heavily used tables may need more frequent checks. Can one surgical table serve multiple specialties?Yes — a modular table with interchangeable tops (orthopedic, urology, carbon-fiber imaging, bariatric) lets a single base cover multiple specialties. This is one of the most effective ways to lower total cost of ownership. Choose a Table Built for the Long Run Selecting a surgical table is a decision you will live with for over a decade. Define your case mix first, then evaluate load capacity, positioning, imaging compatibility, modularity, drive system, cleanability, and certifications against that reality — not against the lowest quote. At VG Medical, we have designed and manufactured surgical tables for more than 20 years, with over 85 patents and products exported to 50+ countries. Our operating tables — including the VCARE 5000 and VCARE 7000 series, and the COMFORT 300 — are MDR CE certified, built on modular platforms, and engineered for precise positioning and easy integration into modern digital OR workflows. Need help specifying the right table for your OR? Contact our team for a detailed positioning specification, C-arm clearance drawings, and a tailored recommendation.
  • Surgical Table Positioning Guide: Safe Patient Positioning for Every Procedure
    Aug 27, 2026
    A practical surgical table positioning guide covering supine, prone, lateral, and lithotomy setups — plus safety checkpoints to protect patients and optimize surgical access. A well-executed surgical table positioning routine is one of the most underrated factors in operative success. Correct positioning gives the surgeon clear access to the surgical site, supports anesthesia management, and protects the patient from pressure injuries, nerve damage, and circulation complications. This surgical table positioning guide breaks down the essentials: how a modern surgical table works, which positions suit which procedures, and the safety checkpoints every OR team should follow.     Why Surgical Table Positioning Matters Patient outcomes are decided long before the first incision — often at the moment the patient is placed on the surgical table. Poor positioning has direct, measurable consequences: Surgical access.An incorrectly angled surgical table can force the surgeon to work against gravity or reposition mid-procedure, extending operative time. Patient safety. Pressure ulcers, brachial plexus injuries, and compartment syndrome are all traceable to inadequate padding and support on the operating table. Imaging compatibility. Procedures that rely on intraoperative C-arm scanning require a radiolucent surgical table — metal components block X-rays and force staff to move the patient. In short, positioning is not a setup task. It is a clinical decision that should be planned the same way the surgical approach is planned. Understanding the Surgical Table: Key Positioning Components Before applying any position, it helps to know what a modern surgical table can actually do. Most electric and electro-hydraulic surgical tables share four core positioning capabilities: 1.      Height adjustment — lowers for safe patient transfer, rises to ergonomically correct working height for the surgical team. 2.      Trendelenburg / reverse Trendelenburg tilt** — pitches the patient head-down or feet-down to shift organs and blood distribution. 3.      Lateral tilt— rolls the table left or right for procedures requiring oblique approaches. 4.      Sectional articulation— independent back, seat, and leg sections enable fusion positions such as flexion, kidney bridge, and beach chair.   Accessories complete the system: positioning pads, headrests, arm boards, straps, and side rails. On tables designed for imaging-intensive procedures, carbon fiber tabletop modules replace standard sections so the C-arm can scan through the patient without repositioning. Common Surgical Positions and When to Use Them Supine (Dorsal) Position The default position for abdominal, cardiac, and many laparoscopic procedures. The patient lies flat on the surgical table with arms secured on arm boards. Reverse Trendelenburg elevates the torso for upper-abdominal access; standard Trendelenberg is used in gynecologic and pelvic surgery. Prone Position Used for spine, posterior cranial, and some orthopedic procedures. Achieving prone safely requires coordinated log-rolling, chest rolls to free the abdomen, and head support that keeps the airway accessible. The surgical table must be set to its lowest height before turning. Lateral Position Common in thoracic, renal, and hip surgery. The patient is turned 90 degrees with an axillary roll under the lower arm and a vacuum mattress or positioning frame to lock the pelvis. Lateral tilt of the operating table fine-tunes surgical exposure. Lithotomy Position The standard for gynecologic, urologic, and colorectal procedures. Leg sections of the surgical table are removed or dropped and legs are placed in stirrups — simultaneously raising them, flexing the hips, and exposing the perineal area. Fowler / Beach Chair Position Back section raised, leg section lowered. Used for shoulder surgery and select ENT procedures. Beach chair position demands strict blood-pressure management because of cerebral perfusion risks. Knee Position Compared with the prone position, the knee position reduces abdominal compression, lowers intra-abdominal and epidural venous pressure, thereby minimizing intraoperative bleeding — especially beneficial for lumbar spine surgery.     Supine Position Abdominal surgery Cardiothoracic surgery  Head and neck surgery Neurosurgery Orthopedic surgery Urological & gynecological surgery Prone Position Posterior spinal surgery  Posterior cranial fossa surgery Anorectal surgery  Achilles tendon repair, posterior leg procedures   Lateral Position Thoracic surgery Renal surgery Total hip arthroplasty Neurosurgery   Lithotomy Position Gynecological & obstetric surgery Urological surgery Colorectal / rectal surgery Perineal surgery     Beach Chair Position Shoulder arthroscopy Rotator cuff repair Total shoulder arthroplasty Acromioplasty, shoulder instability surgery Some ENT/ facial procedures Knee Position Anorectal surgery Sacral/ coccygeal surgery Posterior pelvic procedures Posterior lumbar spine surgery   Step-by-Step Surgical Table Positioning Guide This is the sequence experienced OR teams follow for safe, repeatable positioning: 1. Confirm the procedure and required position with the surgeon before the patient enters the room. Check the surgical table's weight capacity and accessory list against the plan. 2. Prepare the surgical table. Attach section inserts, arm boards, or stirrups. Verify the table is locked, on backup battery if needed, and responsive to the hand control. 3. Transfer at low height. Bring the operating table to transfer height and move the patient with sufficient staff support — this is where most transfer injuries occur. 4. Place the patient, pad the pressure points. Heels, sacrum, occiput, elbows: distribute pressure with gel or foam padding and check that no bony prominence contacts the table frame. 5. Secure limbs and check alignment. Fasten straps without compressing circulation, support the natural curve of the spine, and confirm neutral neck positioning. 6. Adjust table articulation. Apply Trendelenburg, lateral tilt, or sectional flexion in controlled increments, re-checking pressure points after each move — tissue tolerances shift when the surgical table tilts. 7. Verify imaging access. If the procedure uses a C-arm, sweep the arm through the planned arc before draping to confirm clearance and radiolucency. 8. Final time-out. Re-confirm position, padding, and strap placement with the full team before incision. Positioning Safety Checklist Run this checklist after every position change, not just the initial setup: All bony prominences padded, no contact with rigid table parts Eyes protected and free from pressure (prone: check before draping) Arms: abduction under 90 degrees, palms up or neutral Straps secure but distal pulses palpable No limb or trunk crossing hardware or rail edges Cable and accessory routing clear of the patient's skin Surgical table brakes engaged and control functions tested C-arm arc verified before draping (imaging procedures) Choosing a Surgical Table That Supports Positioning Not every operating table makes positioning easy. When evaluating a surgical table for your facility, prioritize: Smooth, quiet electric articulation with a responsive hand control  — jerky movements during Trendelenburg or lateral tilt disturb sterile setup and patient stability. Modular carbon fiber sections for orthopedic and trauma rooms, allowing X-ray and C-arm imaging through the tabletop without repositioning the patient. High weight capacity with low profile — bariatric-safe tables that still drop low enough for safe transfers. Battery backup and quick-release accessories, so positioning never stalls mid-procedure.   As a reference point, VG Medical's VCARE surgical table series combines electro-hydraulic articulation with carbon fiber tabletop options and a full accessory ecosystem for positioning — a configuration typical of what modern OR suites now expect for multi-specialty use.   FAQ What is the purpose of surgical table positioning? Surgical table positioning aligns the patient so the surgical team gets optimal access to the operative site while keeping the patient physiologically stable and protected from position-related injuries such as pressure ulcers and nerve compression. Which surgical position is the most common? Supine (flat on the back) is the most common position on the surgical table, used for abdominal, cardiac, vascular, and many laparoscopic procedures. Lithotomy and lateral positions are the next most frequent. Why is Trendelenburg position used in surgery? Trendelenburg tilts the patient head-down by 15–30 degrees, shifting abdominal organs toward the diaphragm to improve pelvic exposure in laparoscopic surgery and support venous return in selected hemodynamic situations. How does a surgical table affect C-arm imaging? Standard metal table sections block X-rays. Radiolucent carbon fiber sections allow the C-arm to image the patient directly through the surgical table, so imaging can happen during the procedure without repositioning the patient or extending operative time. How often should patient position be checked during surgery? Positioning should be re-verified after every table articulation, and pressure points reassessed at least every two hours for long procedures — tissue perfusion changes as the operating table tilts or the patient shifts under draping. What accessories support safe positioning on a surgical table? Positioning pads, gel heel protectors, arm boards, headrests, stirrups, safety straps, and body straps are the core set. Vacuum mattresses and frame-based positioners are added for prone and lateral cases. Conclusion Consistent, checklist-driven positioning turns the surgical table from a piece of furniture into a clinical instrument. Plan the position with the surgeon, pad every pressure point, re-verify after every articulation, and choose an operating table engineered for smooth, radiolucent, multi-position use. Teams that treat positioning with this discipline see fewer position-related complications and faster, cleaner procedures. Looking for a surgical table built for multi-position surgical workflows? Explore VG Medical's VCARE series — electro-hydraulic positioning, carbon fiber imaging modules, and MDR CE certified manufacturing with 20+ years of OR equipment expertise.        
  • Radiolucent Surgical Table: The Complete Guide for Modern Operating RoomsMeta description
    Aug 24, 2026
       A radiolucent surgical table enables full-body imaging without repositioning the patient Today we will learn how this electric operating table technology works, key buying criteria, and how to choose a raliable surgical table supplier. In modern surgery, imaging is no longer something that happens before or after the operation — it happens during it. Intraoperative fluoroscopy, C-arm navigation, and hybrid OR suites have made real-time visualization a routine part of orthopedic, trauma, vascular, and spinal procedures. The problem? A conventional operating table blocks X-rays at exactly the moment the surgical team needs a clear image. That is where the radiolucent surgical table comes in. Built from advanced carbon fiber and imaging-friendly composites, a radiolucent table allows X-rays, fluoroscopy, and CT scans to pass through the tabletop with minimal attenuation — giving surgeons uninterrupted, distortion-free visualization from skull to femur, without ever moving the patient. In this guide, we break down what makes a surgical table radiolucent, why it matters clinically, and what to look for when evaluating an electric operating table or choosing a surgical table supplier for your hospital or surgical center. What Does "Radiolucent" Actually Mean? Radiolucency is the ability of a material to allow radiation — typically X-rays — to pass through it. Materials with high radiolucency appear dark on imaging; materials that block radiation (like most metals) appear bright white and obscure anatomy. Traditional operating table frames use steel or aluminum. When a C-arm is positioned under a metal-framed surgical table, the frame casts shadows and artifacts into the image. The result: blurry anatomy, repeated exposures, and longer procedure times. A radiolucent surgical table solves this by engineering the patient-contact surfaces — the tabletop, backrest, leg sections, and extension attachments — from carbon fiber composites. Carbon fiber offers an exceptional strength-to-weight ratio while remaining virtually transparent to X-ray beams, permitting imaging across the full length of the table. The Clinical Payoff  Full-body, uninterrupted imaging. Long carbon fiber tabletops (often 1,800 mm or more) allow imaging of the spine, pelvis, and femur in a single setup.  No patient repositioning. Repositioning under anesthesia increases infection risk, breaks sterile field, and adds minutes to every case. With a radiolucent table, the patient stays put.  Lower radiation dose. Clearer first-pass images mean fewer repeat exposures — safer for patients and for the surgical team.  Faster workflows. Continuous imaging supports minimally invasive and fluoroscopy-guided techniques where precision depends on real-time feedback. Where Radiolucent Surgical Tables Earn Their Keep A radiolucent surgical table is not a niche product — it has become standard equipment across a wide range of disciplines: Orthopedics & trauma. From intramedullary nailing to fracture fixation, fluoroscopic control is essential. A radiolucent trauma table allows AP and lateral imaging of the entire lower limb without adjusting the patient. Spine surgery. Pedicle screw placement, kyphoplasty, and deformity correction all demand multi-level imaging. Carbon fiber tabletops paired with 3D C-arms or O-arms deliver clean images across the full spine. Vascular & endovascular procedures. Hybrid ORs combining surgery and interventional imaging rely on tables that support both — radiolucent surfaces compatible with fluoroscopy and angiography systems. Pain management & interventional radiology. Precise needle guidance under fluoroscopy or CT benefits directly from artifact-free imaging surfaces. General surgery. Even outside image-intensive specialties, a versatile surgical table with radiolucent capability future-proofs the OR as imaging-guided techniques expand. Electric Operating Table vs. Manual: Why It Matters More in Imaging Cases Not every radiolucent table is an electric operating table — but for image-guided surgery, electric operation is close to non-negotiable. Here's why: 1.      Precision positioning. Electric, electro-hydraulic systems adjust height, tilt (Trendelenburg/reverse Trendelenburg), lateral tilt, and backrest in smooth, incremental movements — critical when aligning a patient under a C-arm without losing your reference image. 2.     Memory functions. Many modern electric operating tables store position presets, so teams can reproduce exact configurations between cases and quickly return to a verified imaging position. 3.     Hands-free and remote control. Foot pedals and handheld remotes let circulating staff reposition the table mid-procedure without breaking scrub. 4.     Weight capacity with stability. Electric tables typically support patients up to 250–350 kg while maintaining rigidity — essential because flex or vibration under load degrades image quality. The best radiolucent tables combine both: carbon fiber imaging surfaces on a stable, fully electric column. That pairing gives surgical teams the freedom of unrestricted imaging with the ergonomic control of powered positioning. How to Evaluate a Radiolucent Surgical Table: 6 Checklist Items When you compare models — whether from an established European brand or a global surgical table supplier — run every option through this checklist: 1. Material & Imaging Performance Confirm the tabletop is genuine carbon fiber composite, not merely "X-ray compatible." Ask for attenuation data and ask specifically about imaging windows along the full longitudinal axis — not just the center section. 2. Range of Motion Look for generous tilt, lateral roll, slide, and height adjustment. Tables that translate longitudinally make C-arm repositioning faster and safer. 3. Modular Accessories A modular surgical table accepts interchangeable headrests, spine frames, traction units, and arm supports — extending usefulness across specialties. Radiolucent extension and leg sections should be available as options. 4. Weight Capacity & Stability Rated patient capacity of at least 250 kg is today's practical baseline. Check lateral stability at full tilt; a wobbling table ruins both surgery and imaging. 5. Battery & Power Redundancy Built-in rechargeable batteries ensure the electric operating table keeps working during power interruptions or intra-room transfers. Verify battery life per charge cycle. 6. Compliance & Service CE marking under MDR, ISO 13485 manufacturing, and documented electrical safety (IEC 60601) are baseline requirements. Equally important: does the supplier stock spare parts, top cushions, and accessories, and can they support your region? Choosing a Surgical Table Supplier: Beyond the Spec Sheet The table itself is only half the purchase. The other half is the partner behind it. When evaluating a surgical table supplier, weigh: Regulatory track record. MDR CE certification and 20+ years of manufacturing history indicate a quality management system that will still be around for your next order. Product breadth. A supplier that also manufactures surgical lights, ceiling pendants, and ICU equipment can deliver an integrated, compatible OR ecosystem — fewer vendors, fewer integration problems. OEM & customization capability. Hospitals with special requirements (bariatric variants, custom tabletop lengths, specialty traction setups) benefit from suppliers with in-house engineering and OEM experience.  Export experience. Suppliers active in 50+ countries understand logistics, installation support, documentation, and after-sales service across different regulatory regions.   ·        Training and documentation. Clear user manuals, positioning guides, and installation support dramatically shorten onboarding for OR staff. FAQ: Radiolucent Surgical Table Q1: What is a radiolucent surgical table?A radiolucent surgical table is an operating table whose patient-supporting surfaces — tabletop, backrest, and leg sections — are made from X-ray-transparent materials, typically carbon fiber composite. This allows intraoperative fluoroscopy, X-ray, and CT imaging to pass through the table without artifacts, so the patient does not need to be moved for imaging. Q2: How is a radiolucent table different from a standard operating table?A standard operating table uses metal components in the frame and tabletop that block X-rays and create imaging artifacts. A radiolucent surgical table replaces those components with carbon fiber, enabling clear imaging along nearly the entire table length. Functionally, both support patient positioning; only the radiolucent version supports uninterrupted intraoperative imaging. Q3: Which surgeries require a radiolucent surgical table?The strongest need is in orthopedic and trauma surgery, spine surgery, vascular and endovascular procedures, and pain management — anywhere fluoroscopy or C-arm imaging is used during the operation. Many hospitals now specify radiolucent capability for all new tables to keep their ORs future-ready. Q4: Is a carbon fiber surgical table strong enough for heavy patients?Yes. Modern carbon fiber composites are engineered for high load capacity — quality radiolucent tables typically support 250 kg or more. Carbon fiber's strength-to-weight ratio is actually superior to steel; it is the same material family used in aerospace structures. Q5: Should I choose an electric operating table or a manual one for image-guided surgery?For image-guided surgery, an electric operating table is strongly recommended. Electric and electro-hydraulic systems provide smooth, precise, incremental adjustments that keep the patient's imaging position stable during repositioning, plus weight capacity, memory presets, and hands-free control — features manual tables cannot match. Q6: How do I verify a surgical table is truly radiolucent?Ask the supplier for radiographic attenuation test data and request a demonstration with a C-arm if possible. Check that the radiolucent zone covers the full longitudinal axis of the tabletop — including optional extension sections — rather than only a central imaging window. Q7: What maintenance does a radiolucent surgical table need?Routine care includes inspecting carbon fiber surfaces for cracks or deep scratches (which can compromise structural integrity), checking cushion integrity, battery maintenance for electric models, and annual inspection of the column, controls, and brakes by qualified service engineers. Follow the manufacturer's service intervals. Q8: Can one radiolucent surgical table cover all specialties?A modular radiolucent table with interchangeable accessories — headrests, traction bridges, arm supports, and extension sections — can support general, orthopedic, trauma, spine, and vascular procedures. Dedicated specialties (e.g., complex spine deformity correction) may still benefit from specialty-specific frames used in combination with the table. The Bottom Line The shift toward intraoperative imaging has redefined what an operating table must do. A radiolucent surgical table is no longer a premium extra — it is core infrastructure for any OR performing image-guided surgery. When selecting yours, look for full-length carbon fiber imaging surfaces, powered electro-hydraulic positioning, modular accessories, and a surgical table supplier with proven regulatory compliance and long-term service capability. The right table doesn't just hold the patient. It keeps the image clean, the workflow fast, and the surgical team in control — from incision to closure.   Looking for an MDR CE-certified radiolucent surgical table? Explore VG Medical's electric operating table series — carbon fiber imaging surfaces, modular design, and 20+ years of operating room equipment manufacturing experience, trusted in 50+ countries. Contact our team for a configuration matched to your specialty.   Carbon Fiber Board for Surgical table Cabon fiber tabletop enables complete C-arm imaging with zero patient repositioning. Carbon Fiber Board for Surgical table Whatever you needs, CARESTONE is at your side. Carbon Fiber Board for Surgical table Whatever you needs, CARESTONE is at your side.

leave a message

leave a message
If you are interested in our products and want to know more details,please leave a message here,we will reply you as soon as we can.

Home

Products

contact